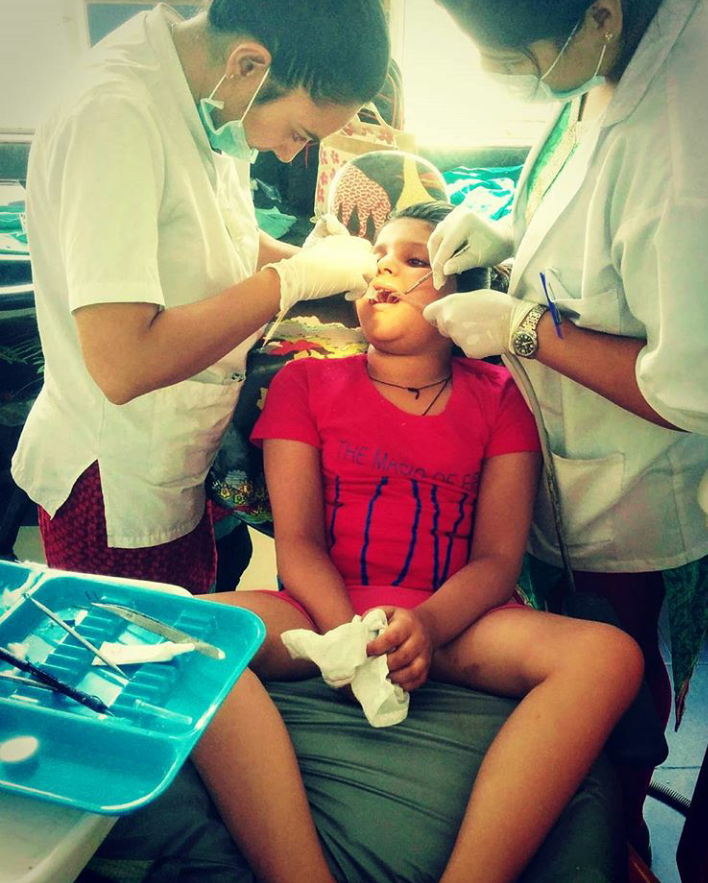
NEED SPECIALTY FOR SPECIAL NEEDS

The National Policy for Persons with Disabilities (2006) recognizes that Persons with Disabilities are valuable human resource for the country and seeks to create an environment that provides equal opportunities, protection of their rights and full participation in society.To facilitate the national objective, there is a need for collection, compilation and analysis of data on disability. 

Eight categories of disability were used in the 2011 census: 1)seeing disability, 2)hearing disability, 3)speech disability, 4) movement disability, 5)mental retardation, 6)mental illness, 7) any other disability, and 8)multiple disability.

The 2014 bill expanded the definition of disability with 19 other conditions which include blindness, low vision, leprosy cured persons, hearing impairment(deaf and hard of hearing), locomotor disability, dwarfism, intellectual disability, mental illness, autism spectrum disorder, cerebral palsy, muscular dystrophy, chronic neurological conditions, specific learning disabilities, multiple sclerosis, speech and language disabilities, thalessimia, hemophillia, sickle cell disease and multiple disabilities including deaf and blindness.

As per Census 2011, in India, out of the 121 Cr population, about 2.68 Cr persons are ‘disabled’ which is 2.21% of the total population.Among the disabled population 56% (1.5 Cr) are males and 44% (1.18 Cr ) are females.In the total population, the male and female population are 51% and 49% respectively.Majority (69%) of the disabled population resided in rural areas (1.86 Cr disabled persons in rural areas and 0.81 Cr in urban areas).In the case of total population also, 69% are from rural areas while the remaining 31% resided in urban areas.

The disability among children is a matter of serious concern as it has wider implications.The Census 2011 showed that, in India, 20.42 lakhs children aged 0-6 years are disabled.  Thus, one in every 100 children in the age group 0-6 years suffered from some type of disability. 1.24% of the total children (0-6 years) are disabled. The percentage of male disabled children to total male children is 1.29% and the corresponding figure for females is 1.19%.The proportion of disabled males to total males is higher than the corresponding proportion for females at all India and at rural and urban areas.The same pattern has been observed in the case of children (0-6) years.Of these 23% of the disabled children (0-6 years) are having disability in hearing, 30% in seeing and 10% in movement.7% of the disabled children have multiple disabilities. A similar pattern is observed among male and female disabled children.

Studies of literature show that children with special needs receive inadequate oral health care when compared to the non disabled population.What makes it more ominous is the fact that children with special needs have a higher incidence of dental caries, periodontal disease or dental trauma.The encumbrance of the oral disease in these individual adds to the existing psychological, emotional and financial burden caused by the already existing medical condition the corresponding figure for females is 1.19%.The proportion of disabled males to total males is higher than the corresponding proportion for females at all India and at rural and urban areas.The same pattern has been observed in the case of children (0-6) years.Of these 23% of the disabled children (0-6 years) are having disability in hearing, 30% in seeing and 10% in movement.  7% of the disabled children have multiple disabilities.A similar pattern is observed among male and female disabled children.

Inclusive health for all should not just be the provision of health services but it should ensure that people with disability along with others who are disadvantaged,and discriminated by society receive the due health services so that they can contribute to the overall development of a community.

ROLE OF ACID AND DENTIST ON ACID ATTACK

Acid attack is defined as the act of throwing acid onto the body of another with the intention to disfigure, torture, or kill. An acid attacker throw acid at their victims, usually at their faces, burning and damaging skin tissue, often exposing and sometimes dissolving the bones.These effects the lives in many more ways then just psychological, social and economical. Burn patients develop a very low self esteem due to pain, social stigma and they lose hope to live.

About 1,500 acid attacks are reported  worldwide every year, according to U.K.based charity Acid Survivors Trust International. In India, about 350 cases are legally reported per year, while separate research conducted by an organization Acid Survivors Foundation India, estimated approximately 500–1000 cases per year in India, excluding unreported incidents.This is an alarming situation of increasing incidences where the majority of victims are women (72% )and attacks are often carried out by family members or other related.

Medical and Dental Effects :

The medical effects of acid attacks are extensive. Majority of acid attacks are aimed at the face, and the severity of the damage depends on the concentration of the acid and the time of exposure to the time when it is washed off with a neutralizing agent. Once acid is in contact with skin, acid melts skin tissue and soft tissues exposing the hard tissue or leading to the loss of eyes, ear, nose causing permanent damage.Of these include deformed skull and hair loss, deafness,burned or deformed eyelids, leaving the eyes extremely dry and prone to blindness,shrunken and deformed nose and chin,scarring of the neck. The scars may sometime run downward, welding the chin to the neck or chest.

Mouth becomes shrunken and narrow, and it may lose its full range of motion. Sometimes, the lips may be partly or totally destroyed, exposing the teeth. Eating and speaking  can become difficult. Hydrochloric, sulphuric acid, nitric acid are more readily commercially available acids known to cause these deleterious effects. Even in low concentrations soft tissue dissolved in one hour, the teeth became yellow as the acid reaches the tooth, disintegration of apical third of the tooth occurs in 5 hours, and the tooth is shown to be completely dissolved in 8 hours. Sulphuric acid, mostly affects soft tissues while hydrochloric acid dissolves hard tissue more rapidly compared to nitric acid and sulphuric acid.

Restricted airway in acid burn patients is commonly seen if victim inhales acid vapors creating respiratory problems, In addition to these above-mentioned medical effects, acid attack victims face the possibility of septicemia, renal failure, skin pigmentation, and even death.

Infection is a major danger because the dead tissue around deep burns becomes easily infected. Infection may spread to the healthy part of the skin, and may even kill the victim thus the wounds need to be kept clean and long term antibiotics need to be given to fight infection.The urgent reduction of the chemical load on the skin by surgical debridement is considered to limit the damage of these devastating injuries.Post-burn reconstruction is provided based on functional and aesthetic demands. Priority of the reconstructive care is to restore as much as possible the patient to optimum form and function.The conventional treatment consist of immediate and continuous water lavage for 2–3 days, then followed by excision surgery and grafting within one week if necessary.

Scars may also grow over the nostrils or ear canals, and surgery is required to remove them. Custom made splint are used to apply direct pressure over the wound site, preventing the excess formation of collagen fibers and realigns them in a normal pattern minimizing the formation of hypertrophic scars. As the scars thicken and contract, they can cause permanent disability by stiffening temperomandibluar joints and restricting movement leading to difficulty in swallowing.Doctors may need to perform many operations to release the scars and graft new skin over them.Jaw reconstruction and fracture rehablitation may be required in subsequent surgeries to rebuild form and function.Software have been used to employ a 3D motion tracking laser scanner and computer‐aided designing done to provide a custom burn mask to the patient without contacting patient’s skin

Minor procedures include simple grafts for eyelid contractures, hair transplants and z-plasties. Major procedures include free tissue transfer, tissue expansion and major facial resurfacing procedures.Priority is always given to eye closure, oral continence, neck and limb movement. Surgery is also offered for resurfacing, hair transplantation and aesthetic nasal reconstruction.The American Academy of Facial and Reconstructive Surgery and American Academy of Cosmetic Dentistry sponsored two projects “Face to Face” and “Give back a Smile.” This group works in partnership with the National Coalition Against Domestic Violence to repair facial and dental injuries of victims of domestic and dating violence.

Anaplastology is a branch of medicine dealing with the prosthetic rehabilitation of an absent, disfigured, developmental, and acquired defects like: nasal prosthesis, ocular prosthesis, finger prosthesis, calvarian reconstruction. Various alloplastic materials are most commonly used for cranioplastic reconstruction which includes tantalum, titanium, stainless steel(austenite), vitallium. With the evolution of acrylic resins, silicone, and polyethylene, metals have been used less. Heat polymerized polymethyl‑methacrylate and high‑density porous polyethylene (HDPE) which is available in various shapes and forms is found to be an excellent alternative with good flexibility to be molded into desired contours.

Recent advances in maxillofacial dentistry have increased demand for prosthetic rehabilitation of acid attack victims with the team work of oral and maxillofacial surgeons and maxillofacial prosthodontist and ortodontist. Prosthetics are a quick, reversible, and medically uncomplicated procedures with the advantage that the restoration may be readily removed to allow evaluation of the health of underlying tissue. Technological advancement has a profound impact on the maxillofacial restoration of form and function.Patients should be provided good counseling support as the long course of treatment. There are several instances when acid burn patients have bounced back in life. Therefore it is essential for the mental and physical well being of acid attack victim that every effort should be made to restore as much of the facial profile in order to keep their self dignity intact.

KEEP THAT GAMEFACE ON AND FIGHT LIKE A PRO

We are all confused souls waiting to find the reason for our lives,willing to use all our chances before we get consumed by the black hole.I was once “your answer to the matrix”,(my personal description on social sites.)now I am stuck in the matrix myself.

But we evolve,and that’s how we survive.We don’t stop and that’s how we grow.When we are given colors we scribble into our imaginary world; when we hold pens we make the best bachelors ,when we start working we accomplish task and when we get to share our experience we have stories to tell.

This post stems from a problem for which we have to find a solution. Looking at the facts,we found tooth loss in people under 35 is most commonly caused by athletic trauma,fights or accidents.A non expensive tool that is available and is a possible way to protect your face from many injuries that your teeth and jaw suffers while playing, gym training on the ground and practicing contact sports. The injuries that require life long care and expenses and could be easily averted had we been aware and asked questions.

The National youth sports foundation for the prevention of Athletic injuries has
reported that dental injuries are the most common type sustained during participation in sports.Most of these injuries can be reduced or at least prevented with the use of proper equipment like a guard.A mouth guard is a soft plastic or laminate device used in sports to prevent oral injuries to the teeth,mouth, cheeks, tongue and jaw.According to different reports, sports-related facial fractures account for 20% of all sports injuries and as much as 33% of all facial bone fractures.The use of a mouth guard can prevent more than 200,000 oral injuries to the mouth each year.

This post intend to create awareness towards parents and the youth that protecting your teeth and jaws are your absolute right and every school should make mouth guards a mandatory requirement for all contact sports and training.It is as much a school responsibility as of the parents when their children opt for contact sports as activities. All contact sports like basketball, baseball, wrestling,mixed martial arts,soccer and volleyball may consider wearing a mouth guard to prevent injuries to the mouth.Just like camps for dental checkup and medical vaccination,schools can coordinate with their local dentist for mouth guard impression every new semester and bring them into continual care and safe sports.

For me it will always be “no guard no play”.All that is required is you fixing up an appointment with your dentist specialized in making mouth guards for your requirement. Over the counter available mouth guards are “one size fits all” can not provide adequate protection because your jaw is not like others.

“You can prevent accidents or you can pay for a broken smile”

My First Open Letter To The Prime Minister

Little enthusiastic butterflies when they leave the cocoon, uses their wings to explore the gardens. They don’t realize that their wings are only for the sub and not for the big adventures.They called it hard luck, I call it misplaced optimism of the doom.

Few years ago I got excited to learn about the OPEN LETTER DAY .The interesting concept that make your hope become like NASA scientist discovering a new sustainable planet. It was my daily commute to college during my post graduation days when I heard this narration by a radio jockey on how prime minister acted upon the letters of a common-man and how they had became an overnight sensation. People like duchess of Sussex,Meghan Markel who are outspoken feminist contributed into this aggressive attempt of making my voice heard .She had then addressed the issue of gender equality.”Women are fighting greasy pots and pans..” if you know what I mean.

My emotions at that time was boiling like spilling milk as I penned down my feelings writing my first ever  letter to SHRI NARENDRA MODI JI. Not for the job or MoU for foreign dental education. Not even better conveyance because clearly I am in awe of the metro connectivity in Delhi,NCR which is at par with south Korea.

In my letter I appealed for special need dentist training and facility. Even Google doesn’t points to exclusive Special Needs dentist. That letter still remains untouched and unseen on LinkedIn and it read something like this,

“This letter sends in words of appreciation and thanks for your services to my India.As I may bring to the status of dentistry that has become a business or where the ratio of dentist to patient(now called as clients)is never reached, what is more discouraging is that we don’t have good dental care for special needs patients.There is special needs training for dentist in Los Angeles with the name of UCLA but I cant find one in India. Sir,as I have treated few patients with the syndrome disorders I realize we need to extend our services to the unmet crowd.I have no idea how I will bring this to reality but I am dedicated and have expertise to work in this direction.hope to learn from you.”

Not one single year of my graduation days we got clinical orientation for managing children with special needs. How is that most essential part of our society doesn’t receive regular dental assessment and treatment and only attended as a complex and complicated patient.We are not prepared to handle even as graduate for basic treatment needs of these patient with fluoride application, preventive resin restoration, atraumatic restorative technique or restorative and rehablitative procedures

Mostly training is limited to post graduate trainee in pediatric dentistry and oral surgery. However the curriculum doesn’t includes exclusive exposure to special needs patient for efficient management and depends on OPD basis only. As a result of which most of the times doctor are not equipped and neither inclined to treat the patient.

These thoughts continued to reverberate post my college years until I landed into this really cool job at the most expensive area of New Delhi. When did I end up being a hygienist from a pediatric dentist, a question that keeps nagging in my head every single day since. The probability of me being a special needs dentist looks like a distant future. It is gut wrenching feeling when your dreams and reality have an employer and employee like gap.But not getting your voice heard is still more saddening.

Our PM may just happen to peak someday on the mention of his name and know thereof that if there is one group that does not get routine quality care it is this special needs and disability.It is good to hear that pedodontist are talking about it now. Hopefully we will have fellowship and training center along with satellite dispensary and backup hospital to streamline these patient and they get continual care.

Till then I must continue to apply in international colleges for specialist training in special needs.I fathom in the ambiguity however,when will we get the dental services and care to the deferentially able here.

Create your own website, free on WordPress.com.Create your own website.
Start free